
Do natural redheads really need more anesthesia? How surgical trials, 1,000 Genomes, and pain panels detangled the myth
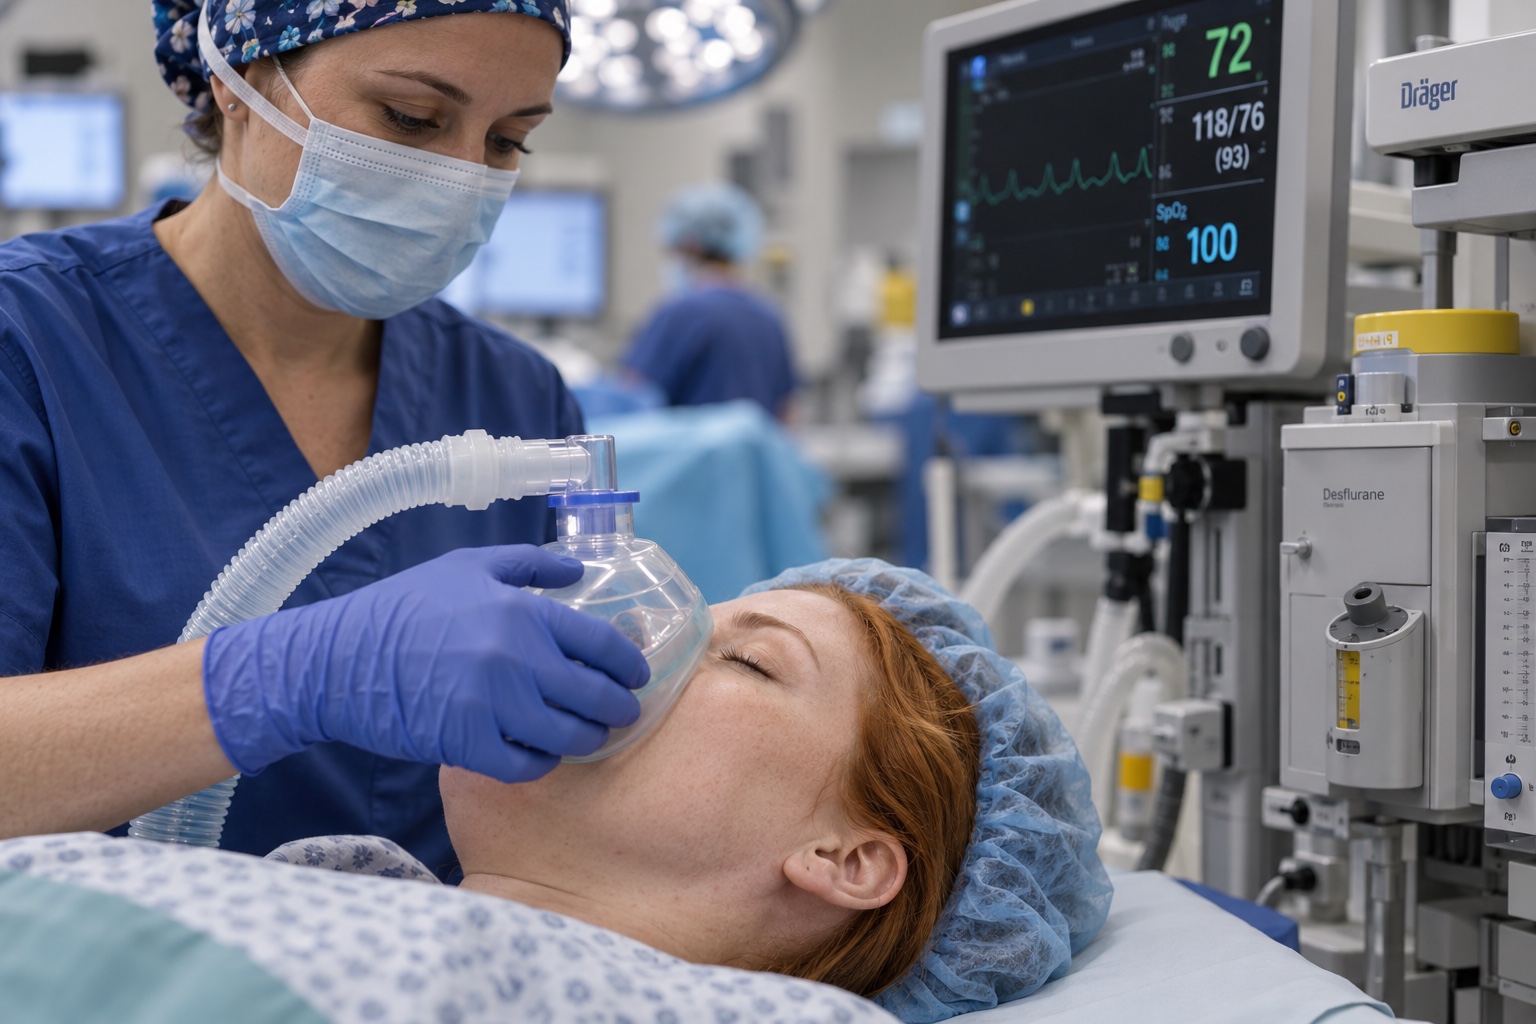
For two decades, the claim that natural redheads require 19% to 20% more anesthesia has circulated widely across social media, popular press, patient discussion groups, and clinical folklore. Traced to its source, the number originated from an August 2004 laboratory experiment published in Anesthesiology by University of Louisville investigators. The preliminary study examined just twenty healthy female volunteers breathing volatile desflurane while receiving noxious electrical shocks and observed a 19% higher minimum alveolar concentration (MAC) to suppress reflexive movement.
However, when anesthesiologists tested this hypothesis in real-world clinical surgery, they could not replicate the alleged redhead effect. In a prospective matched cohort study of 468 adult surgical patients published in Anaesthesia and Intensive Care by researchers at Monash University and The Alfred Hospital, investigators compared natural redheads directly against matched black- and brown-haired patients undergoing elective surgery. The study recorded the anaesthetic drugs and doses used, depth of anaesthesia, recovery times, pain scores and quality of recovery. It found no evidence that hair colour affects anaesthetic requirements or recovery.
Genomic Architecture: The main red-hair variants are not the ones linked to pain, but the same gene, MC1R, affects both hair colour and pain sensitivity
Studies of pain in redheads have given mixed results, which led geneticists to examine the gene in high resolution. The melanocortin-1 receptor (MC1R) gene on chromosome 16 is the primary genetic driver of red hair and fair skin. Published in PAIN, a landmark study titled Detangling Red Hair from Pain, geneticists from McGill University and Duke University tested every genotyped MC1R variant for links with pain sensitivity in a pain cohort, then checked their results in 500,000 UK Biobank participants.
Crucially, the genomic evidence demonstrated that MC1R is relevant to pain. But the gene plays distinct dual roles through different genetic mechanisms:
- Pigment loss-of-function coding mutations: Classic missense variants including R151C (rs1805007), R160W (rs1805008), and D294H (rs1805009) disrupt G-protein-coupled signalling in dermal melanocytes, blocking the switch from red-yellow pheomelanin to brown-black eumelanin.
- Pain-linked variants: rs3212361, a variant in the gene's 5' untranslated region that lowers MC1R expression in brain and nerve tissue, and rs885479 (R163Q), a milder missense variant only weakly tied to red hair. Their minor alleles were linked to lower pain sensitivity.
The authors emphasised that these regulatory markers are viable candidates for inclusion in precision pain sensitivity panels to tailor analgesia. The study also found that the strong red-hair variants, such as R151C, R160W and D294H, were not linked to pain sensitivity. Only rs3212361 and the mild variant rs885479 were, and rs3212361 was itself associated with red hair. In UK Biobank, people with red hair reported fewer persistent pain conditions than people with dark hair.
Empirical Population Segregation in the 1,000 Genomes Project
We went down this rabbit hole, and that made us question how the initial study by Liem et al. 2004 found such a strong relationship between red hair and pain. Was it an artifact of small sample size and ancestry? We tested how these alleles segregate across human populations by analysing high-coverage 1,000 Genomes Project whole-genome data for 2,590 adults from 26 populations. The empirical data highlight profound continental and sub-continental stratification across MC1R alleles:
| Genomic Position (GRCh38) | rsID | Codon / Effect | Biological Type | British (GBR) | NW Euro (CEU) | Finnish (FIN) | Iberian (IBS) | Italian (TSI) | European (EUR) | African (AFR) | East Asian (EAS) |
|---|---|---|---|---|---|---|---|---|---|---|---|
| chr16:89919436 | rs1805005 | V60L | Partial Loss / Fair | 11.7% | 7.8% | 5.1% | 15.4% | 16.4% | 11.2% | 0.5% | 0.0% |
| chr16:89919532 | rs2228479 | V92M | Partial Loss / Fair | 11.7% | 6.6% | 5.6% | 5.1% | 6.1% | 6.9% | 0.4% | 29.3% |
| chr16:89919683 | rs11547464 | R142H | Functional Loss | 0.0% | 0.0% | 1.0% | 2.8% | 0.5% | 0.9% | 0.1% | 0.0% |
| chr16:89919709 | rs1805007 | R151C | Strong Red Hair (r) | 10.0% | 12.3% | 8.6% | 3.3% | 2.3% | 7.3% | 0.3% | 0.1% |
| chr16:89919736 | rs1805008 | R160W | Strong Red Hair (r) | 7.2% | 10.7% | 8.1% | 0.9% | 4.7% | 6.4% | 0.4% | 0.0% |
| chr16:89920138 | rs1805009 | D294H | Strong Red Hair (r) | 0.6% | 0.4% | 0.5% | 1.4% | 0.9% | 0.8% | 0.1% | 0.0% |
| chr16:89920793 | rs3212371 | 3'UTR | Non-coding Regulatory | 13.9% | 8.2% | 5.6% | 10.3% | 8.9% | 9.2% | 32.2% | 29.6% |
In our analysis, British samples (GBR, representing Celtic and Anglo-Saxon ancestry) showed 30.0% of individuals carrying at least one strong red-hair allele, with 5.6% exhibiting compound homozygosity (r/r) that confers the classic red-hair phenotype. In Northern/Western European ancestry (CEU), carrier frequency reaches 40.2% (6.6% r/r). In contrast, carrier frequencies drop to 11.2% in Spain (IBS) and 15.0% in Italy (TSI), and are rare in African (1.6%) and East Asian (0.2%) samples. The CEU group are Utah residents, so the highest figure is itself an American sample. Among other US-based samples, 11% of African Americans in the Southwest and 9% of Puerto Ricans carry one.
Our linkage analysis in the same data found that R151C (rs1805007) and R160W (rs1805008), only 27 base pairs apart, never occur on the same chromosome copy in our European adults (0 of 1,050 chromosomes). They arose on different historical haplotypes, so a person with red hair carries either two copies of one variant or one copy each of two different variants, one from each parent. In the same European data, every chromosome carrying R160W also carried the pain-linked rs3212361 allele, while no chromosome carrying R151C did.
The Ancestry Hypothesis: Are Europeans or Celtic Cohorts More Pain Sensitive?
This sharp geographic segregation may help explain the 2004 laboratory study. When researchers select subjects on the basis of bright red hair in places like Kentucky, they are not merely selecting a pigment mutation; they are isolating a cohort with dense Celtic and Scots-Irish ancestry in an admixed population with a diversity of people from different genetic backgrounds.
Could that ancestry carry its own differences in pain sensitivity? The PAIN study could not answer this, because it included only people of European ancestry and adjusted every analysis for ancestry. So we checked two well-studied pain genes in the same data. Between continents they differ a lot: the COMT variant (rs4680) linked to lower pain thresholds is on 52% of British chromosomes but 28% of African and East Asian ones, and the OPRM1 opioid receptor variant (rs1799971) ranges from 1% in African samples to 39% in East Asian samples. Within Europe the differences are small. The COMT variant sits between 45% and 52% in British, northwest European, Spanish and Italian samples, and British samples carry the OPRM1 variant least often (12%, against 15% to 18%). These two genes alone are therefore unlikely to explain the 2004 result, which came from twenty people and measured a reflex response to electrical stimulation, not surgery.
Clinical Practice: Anesthesia is Titrated, Not Prescribed by Hair
In modern operating theatres, volatile anesthetics such as desflurane, sevoflurane, and isoflurane act broadly on central nervous system targets, including GABA_A receptors, two-pore domain potassium channels (K2P), and hydrophobic neuronal membrane cavities. They do not depend on melanocortin signalling.
Anaesthetists do not set the dose by hair colour. Clinical anesthesia is titrated continuously in real time to the patient's physiological and neurological feedback:
- Processed Electroencephalogram (EEG) Monitoring: Systems such as the Bispectral Index (BIS) monitor cortical brainwave activity to ensure adequate depth of unconsciousness.
- End-Tidal Anesthetic Gas Concentration (EtAG): Infrared gas analysis measures exact exhaled agent concentrations in real time.
- Hemodynamic Response: Continuous monitoring of blood pressure, heart rate, and heart rate variability detects autonomic responses to surgical stimulation before consciousness can emerge.
Patients with natural red hair can undergo surgery with complete confidence. The 20% extra "ginger anesthesia" requirement was a twenty-year myth: the surgical evidence does not support it, and the original result came from a study of twenty people. The PAIN study points to MC1R pain variants as candidates for pain sensitivity panels that could improve care for everyone.
Written by the Genomes desk from the primary sources cited and linked above and checked against them. Research use only; not medical advice. Corrections: [email protected].